
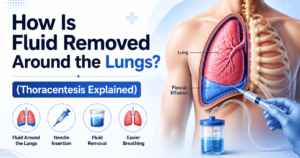
This guide explains exactly how fluid around the lungs is removed, what each procedure involves, what to expect during recovery, and when you should see a specialist.
What Is Fluid Around the Lungs?
Understanding the Pleural Space
Think of your lung as a balloon sitting inside a slightly larger plastic bag. The inner layer of that bag is pressed against the lung; the outer layer lines the chest wall. The tiny gap between the two layers is the pleural space, and it normally holds a small amount of fluid — just enough to let the lung slide smoothly as you breathe.
When something disrupts that balance, fluid builds up faster than the body can absorb it. This is pleural effusion.
There are two main types:
- Transudative effusion — caused by increased pressure in blood vessels or low protein levels (common causes: heart failure, liver cirrhosis, kidney disease). The fluid leaks out of blood vessels.
- Exudative effusion — caused by inflammation, infection, or cancer. The fluid is richer in protein and cells. Common causes include tuberculosis (TB), pneumonia, and lung cancer.
Knowing the type matters because it guides both the drainage method and the treatment of the underlying cause. In India, tuberculosis is one of the most frequently identified causes of exudative pleural effusion — making accurate diagnosis especially important.
When Does Fluid Need to Be Removed?
Not every pleural effusion requires immediate drainage. Your doctor’s decision depends on the amount of fluid and the symptoms it is causing.
Watchful waiting may be appropriate when:
- The effusion is small and detected incidentally on imaging
- You have no significant breathing difficulty
- Treating the underlying cause (such as diuretics for heart failure) may resolve it on its own
Drainage is usually recommended when:
- You experience shortness of breath, chest tightness, or difficulty breathing at rest
- The effusion is large or growing
- The cause needs to be identified through fluid analysis
- The fluid has become infected (empyema) or is associated with a malignancy
So — can fluid around the lungs go away on its own? For small transudative effusions, yes, treating the root cause often resolves it without any drainage procedure. But moderate to large effusions, and most exudative effusions, typically require active management. Your pulmonologist will advise based on your individual case.
How Is Fluid Removed Around the Lungs?
There is no single answer to how fluid around the lungs is removed — the right method depends on the amount of fluid, the likely cause, whether it is likely to recur, and your overall health. Here are the main options, explained in plain language.
Thoracentesis (Pleural Tapping) — The Most Common Method
Thoracentesis (also called pleural tapping in Indian hospitals) is the most frequently performed procedure for draining fluid around the lungs. It is minimally invasive, does not require surgery, and is usually done as a day procedure.
What happens, step by step:
- You sit upright on a bed or chair, leaning slightly forward with your arms resting on a support.
- Your doctor uses an ultrasound scan to locate the fluid precisely — this makes the procedure safer and more accurate.
- The skin on your back or side is cleaned and a small amount of local anaesthetic is injected to numb the area.
- A thin needle or catheter is inserted between two ribs into the pleural space. The sensation is often described as pressure rather than sharp pain.
- The fluid is drained into a collection bag or syringe. Typically, between 1 and 1.5 litres is removed in a single session, though this varies.
- The needle is removed and a small dressing is applied.
- A chest X-ray is taken afterwards to confirm the fluid has been removed and the lung has expanded normally.
The whole procedure usually takes 20 to 30 minutes. Most patients go home the same day.
The fluid removed is sent to a laboratory for analysis — this is how doctors identify the cause of the effusion (infection, cancer cells, TB, etc.), which is just as important as the drainage itself.
Regarding pain: thoracentesis is performed under local anaesthesia. The injection to numb the skin can sting briefly. During drainage, you may feel pressure, the urge to cough, or a pulling sensation. Significant pain during the procedure should be reported to your doctor immediately, as it can signal a complication.
Intercostal Chest Drain (ICD)
An intercostal chest drain (ICD) is a small tube placed between the ribs into the pleural space. It is connected to a drainage bag or bottle and left in place for a period of hours to days, allowing fluid to drain gradually.
Your doctor may recommend an ICD instead of thoracentesis when:
- The amount of fluid is very large
- The fluid is thick, infected, or loculated (divided into pockets that a needle cannot fully drain)
- Continuous drainage over time is needed
- The effusion is associated with empyema (infected pleural fluid)
The tube is inserted under local anaesthesia and sometimes mild sedation. Most patients find the presence of the tube uncomfortable rather than painful. Once the target volume has drained and imaging confirms improvement, the tube is removed — usually under local anaesthesia, with minimal discomfort.
Indwelling Pleural Catheter (IPC) — For Recurring Fluid
For patients whose pleural effusion keeps returning — particularly those with cancer-related effusions — an indwelling pleural catheter (IPC) offers a long-term solution.
An IPC is a soft, flexible tube placed semi-permanently into the pleural space through a small incision. The external end is tunnelled under the skin and capped when not in use. Patients or caregivers can then drain the fluid at home, typically every few days, using a vacuum bottle kit. This avoids the need for repeated hospital visits for drainage.
IPCs are particularly suitable for:
- Malignant pleural effusions (cancer-related fluid)
- Patients who are not candidates for pleurodesis
- Patients who prefer to manage drainage at home
The IPC is placed as a day procedure and training is provided to the patient and family before discharge.
Pleurodesis — Sealing the Space to Prevent Recurrence
Pleurodesis is a procedure designed to prevent fluid from coming back. Rather than simply draining the fluid, pleurodesis causes the two layers of the pleura to stick together permanently — eliminating the space where fluid can collect.
It is performed by instilling a chemical agent (most commonly sterile talc, or sometimes doxycycline) into the pleural space, either through a chest drain or during thoracoscopy. This triggers inflammation that causes the layers to fuse.
Pleurodesis is typically recommended for:
- Recurrent malignant pleural effusions
- Cases where fluid has returned multiple times despite repeated thoracentesis
- Patients who are otherwise well enough to tolerate the procedure
It is not a first-line option — it comes into consideration once drainage alone proves insufficient.
Surgery (VATS) — When Other Methods Are Not Enough
Video-Assisted Thoracoscopic Surgery (VATS) is a minimally invasive surgical approach occasionally used when other drainage methods have failed, or when a direct look inside the chest is needed to take biopsies and treat the pleural space simultaneously.
Most patients with pleural effusion will never need surgery. VATS is reserved for complex or treatment-resistant cases — for example, a trapped lung with a thickened pleural rind, or cases where thoracoscopy (done as an outpatient procedure) is insufficient.
If surgery is recommended, your pulmonologist will refer you to a thoracic surgeon and discuss the procedure, risks, and recovery in detail. View our Thoracoscopy service →
What Happens After Fluid Is Removed?
Recovery after pleural drainage is generally quick, especially for thoracentesis. Here is what to expect:
After thoracentesis:
- You will rest for an hour or two while your blood pressure and breathing are monitored
- A chest X-ray confirms the procedure went well
- Most patients go home the same day
- Mild soreness at the puncture site is normal for 1–2 days
- Avoid strenuous activity (running, heavy lifting, swimming) for a few days
- Air travel should be discussed with your doctor before you plan to fly — your doctor will advise based on how the procedure went and whether there were any complications
- Follow up as your doctor advises — usually within 1–2 weeks
After intercostal chest drain:
- You will remain in hospital while the drain is in place (hours to days)
- Mobility is encouraged — walking with the drain is usually fine
- Once the drain is removed, recovery is similar to post-thoracentesis
- Return to normal activity within a few days, subject to your doctor’s guidance
After an indwelling pleural catheter (IPC):
- You will receive detailed instructions on caring for the catheter and draining at home
- Regular follow-up is essential to monitor for infection and lung expansion
- The catheter may be removed if spontaneous pleurodesis occurs (the pleural layers fuse naturally over time)
Warning signs — seek medical attention immediately if you notice:
- Sudden worsening of breathlessness
- High fever or chills
- Significant pain at the drain or catheter site
- Redness, swelling, or discharge from the wound
Will the Fluid Come Back?
Whether pleural fluid returns depends almost entirely on whether the underlying cause has been treated.
- If the effusion was caused by a chest infection or pneumonia and the infection is cleared, fluid is unlikely to return.
- If it was caused by heart failure and your cardiac condition is well controlled, recurrence is less likely.
- If it is related to cancer or a chronic condition, fluid may continue to accumulate — which is why long-term management options like IPC or pleurodesis exist.
Drainage alone does not cure pleural effusion. The most important step is identifying and treating the root cause. Your pulmonologist will coordinate this alongside the drainage procedure.
If you have Interstitial lung disease or Early signs of lung cancer, which can both be associated with pleural effusion, early specialist review is especially important.
Frequently Asked Questions
Is draining fluid from around the lungs painful?
Most patients experience mild discomfort rather than significant pain. A local anaesthetic is used to numb the skin and underlying tissue before any needle or tube is inserted. You may feel pressure, the urge to cough, or a pulling sensation during drainage. Sharp or severe pain during the procedure is uncommon and should be reported to your doctor immediately.
How long does thoracentesis take?
Thoracentesis (pleural tapping) typically takes between 20 and 30 minutes from start to finish, including preparation and post-procedure imaging. The actual fluid drainage often takes less than 15 minutes. Most patients are discharged on the same day, usually within 2–4 hours of the procedure.
Can pleural effusion go away without drainage?
Small pleural effusions — particularly transudative ones caused by heart failure or kidney disease — may resolve on their own once the underlying condition is treated (for example, with diuretics). However, moderate to large effusions, infected fluid, or effusions causing breathlessness often require active drainage. Your doctor will determine the best approach based on your scans and symptoms.
How much fluid is removed during thoracentesis?
The volume removed varies depending on the size of the effusion and the patient’s tolerance. Typically, between 1,000 and 1,500 ml (1 to 1.5 litres) is drained in a single session. Removing too much fluid too quickly can cause a complication called re-expansion pulmonary oedema, so your doctor will monitor you carefully throughout.
How soon can I return to normal activity after the procedure?
After thoracentesis, most patients return to light daily activity within 1–2 days. Strenuous exercise, heavy lifting, and swimming should be avoided for at least a week. If you are planning to fly, speak to your doctor first — they will advise based on how your procedure went and whether any complications occurred. Your pulmonologist will provide specific guidance based on your recovery and the underlying condition.
When should I see a doctor about fluid around the lungs?
See a doctor promptly if you experience unexplained shortness of breath, a dry cough that does not improve, chest pain that worsens when breathing deeply, or feeling breathless when lying flat. These are common symptoms of pleural effusion. Early diagnosis allows for faster treatment and helps identify any serious underlying cause.
See a Pulmonologist — Your Next Step
Understanding how fluid is removed around the lungs is an important first step — but an accurate diagnosis and the right treatment plan come from a specialist evaluation.
If you or someone you care for is experiencing breathlessness, chest discomfort, or has been told there may be fluid around the lungs, prompt assessment by a pulmonologist is important. Early intervention leads to better outcomes and prevents complications.
Dr. Sumita Agrawal is a DM Pulmonologist and Head of the Department of Pulmonary, Critical Care & Sleep Medicine at Jodhpur. She provides the full spectrum of interventional pulmonology procedures — including thoracentesis, intercostal drainage, and thoracoscopy — with access to advanced imaging guidance and cutting-edge treatment technologies.
If you are in Jodhpur, Rajasthan, or the surrounding region, you can Book a consultation directly.